An anion gap calculator is a practical assessment tool for assessing acidosis of unclear cause and helping narrow the likely cause of an acid base disorder. By arranging common laboratory values from a serum chemistry panel, it allows clinicians and informed readers evaluate whether the pattern suggests high anion gap or typical anion gap metabolic acidemia. The result is not a diagnosis by itself, but it is a fast way to inform clinical assessment, inform next steps, and improve interpretation of the underlying metabolic disturbance.
What the Anion Gap Measures
The anion gap is a derived figure that compares the main measured electrolytes in blood, especially sodium, chloride, and bicarbonate. It is used to estimate the gap between positive and negative particles in the bloodstream. In basic terms, the calculation can reveal whether there are unmeasured acids collecting in the blood, which is central to understanding acid-base balance and identifying an elevated anion gap.
Because the body tightly controls serum sodium, serum chloride, and serum bicarbonate, changes in these values can point to an underlying problem in blood chemistry. For example, if bicarbonate is low and the gap is high, that pattern often points to added acid in the system. If the gap remains within the reference range, the cause may instead stem from direct bicarbonate loss or another process that raises chloride to maintain balance.
Understanding the anion gap is especially useful when a patient has acidosis but the cause is not obvious. It offers a structured way to think about acid accumulation, helps differentiate one type of metabolic acidosis from another, and supports cause identification when symptoms and routine tests do not immediately explain the problem.
How to Determine the Anion Gap
The standard anion gap formula generally uses sodium less the sum of chloride and bicarbonate:
Anion gap = Sodium − (Chloride + Bicarbonate)
This calculation comes from values on a serum chemistry panel, where the key inputs are the measured sodium, chloride, and bicarbonate. Certain versions of the formula also include potassium, but the most widely used approach excludes it. The result gives a fast overview of the charge balance between measured cations and anions.
Albumin matters because it is a major unmeasured negatively charged protein in blood. When albumin is low, the raw anion gap may seem lower than expected even if an acid-base problem is present. That is why many clinicians also use a corrected anion gap to refine interpretation. A careful interpretation considers not only the formula result, but also whether hypoalbuminemia could be hiding a clinically important acid-base problem.
A easy way to think about the formula is this: if the measured bicarbonate drops because acid is present, the gap may widen if the lost bicarbonate is replaced by unmeasured acid anions. If bicarbonate falls because it is being lost directly from the body, chloride often rises to keep electrical neutrality, which can produce a normal gap result instead.
Using an Anion Gap Calculator
An anion gap calculator takes the guesswork out and helps avoid mistakes during laboratory values review. To use it, enter the relevant input values from the blood chemistry report, usually sodium, chloride, and bicarbonate. Certain calculators may also include albumin so they can display a corrected value alongside the raw result.
Once the numbers are entered, the calculator checks the value with the typical reference range. The exact range can vary by laboratory method, but the goal is the same: see whether the gap is low, normal, or elevated. A result above the expected range may suggest a high anion gap process, while a result within range may point toward a different mechanism of acidosis.
Result interpretation should always relate the number to the broader clinical picture. A small shift can matter when symptoms, other tests, or a known illness support a real metabolic problem. A calculator is useful because it quickly organizes the data, but it should be treated as part of the broader clinical assessment, not as a stand-alone answer.
Useful advice: use the calculator as a screening step. Then compare the result with symptoms, albumin level, and if available, an arterial blood gas to understand whether the acid-base imbalance is truly significant.
Origins of Increased Anion Gap Metabolic Acidosis
Elevated anion gap acidic state usually means the body has accumulated unmeasured acids. This is a classic pattern in which bicarbonate is used up buffering excess acid, while the gap widens because the newly formed anions are not directly measured on the standard panel.
One common cause is lactic acidosis, which can occur when tissues do not receive enough oxygen or when metabolism is otherwise disrupted. Lactate builds up as a byproduct of abnormal energy production, leading to acid accumulation. Another major cause is ketoacidosis, where ketone bodies rise significantly, such as in diabetes, prolonged fasting, or severe alcohol-related metabolic stress.
Renal failure is another important cause of an elevated gap. When the kidneys cannot excrete acid effectively, acidic waste products accumulate in the blood. This can produce a widening gap and worsening NAGMA causes acid-base imbalance. Other high-gap causes may include toxins, certain medications, and severe systemic illness, but the major categories above are the most commonly discussed when using anion gap calculator for unexplained acidosis.
The main point is that a high gap suggests added acid rather than just bicarbonate loss. That distinction helps focus the workup. For example, a patient with elevated lactate, ketones, or kidney dysfunction likely has a different treatment path than someone with a normal gap pattern.
Origins of Typical Anion Gap Metabolic Acidosis
A normal anion gap finding, sometimes called chloride-rich acidosis, often indicates direct loss of bicarbonate or impaired bicarbonate regulation rather than generation of new acids. Here, chloride rises to offset the bicarbonate decrease, so the overall gap remains in range even though the patient still has an acid-base disorder.
Diarrhea is a common cause because intestinal fluids contain bicarbonate. When those fluids are lost, the body can develop acidosis from loss of bicarbonate. Renal tubular acidosis is another key cause, since the kidneys may fail to reabsorb bicarbonate or excrete hydrogen ions properly. This can lead to persistent metabolic disturbance even when kidney filtration is otherwise preserved.
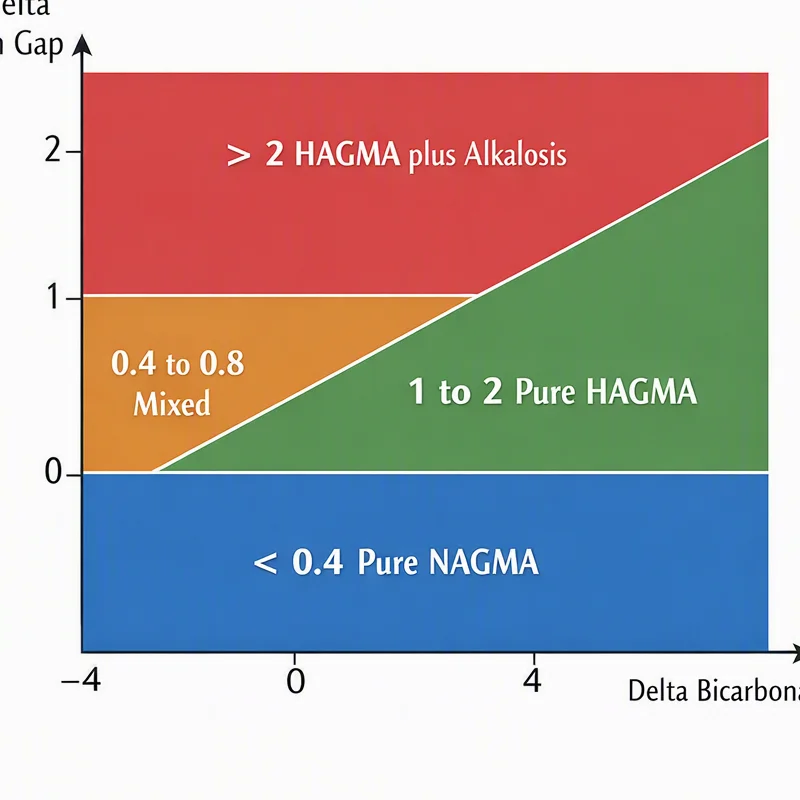
A normal-gap acidotic state is especially important to recognize because the labs may look less dramatic than in a high-gap state. delta ratio use in metabolic acidosis Still, the patient can be seriously affected. The pattern often points to problems in the gastrointestinal tract or kidneys, and the clinical context helps differentiate those possibilities.
Albumin Correction and Why It Matters
Albumin is a key determinant of the measured anion gap because it carries negative charge. When albumin is low, there are less unmeasured anions in the blood, so the raw result may downplay the true burden of acid. This is why hypoalbuminemia can create a deceptively normal or only mildly elevated value.
A corrected anion gap updates the raw number to account for low albumin and improves interpretation. This correction is important when evaluating unexplained acidosis because a patient with substantial acid accumulation may appear less abnormal on the chemistry panel if albumin is reduced. In other words, the raw number may overlook the degree of disturbance.
Understanding protein binding helps explain why this matters. Albumin acts as a buffer and plays a role to the pool of unmeasured anions. If that pool shrinks, the gap can vary even without a change in the primary acid-base problem. This creates one of the most common interpretation pitfalls in routine lab review.
Using the corrected value helps decrease missed diagnoses and supports better cause identification. It is especially useful when the clinical picture suggests significant illness, but the anion gap seems less impressive than expected. In that situation, low albumin may be hiding a meaningful disorder.
How to Interpret Findings in Medical Context
The anion gap is especially useful when it is considered alongside an arterial blood gas, notably the measured pH. A low pH shows acidemia, while the gap helps clarify whether the issue is from unmeasured acids or from bicarbonate loss with chloride retention. In combination, they offer a more complete picture of the patient’s acid-base balance.
Further important clues include the base deficit, which indicates the degree of acid-base acid burden, and the patient’s clinical symptoms. Dyspnea, confusion, emesis, dehydration, loss of strength, or reduced perfusion may all support a medically important problem. The calculator result should be interpreted alongside the clinical picture with the physical examination, medical history, and trajectory of the laboratory values.
For instance, a individual with acidic blood, high lactate, and an raised anion gap likely has a different cause than a individual with diarrhea, low bicarbonate, and a normal gap. Both can be cases of metabolic acidosis, but the assessment and care steps vary.
It is important to keep in mind that mixed acid-base disorders can occur. A person may have one process that raises the gap and another that lowers bicarbonate or alters pH in a different direction. This is why the anion gap calculator is a diagnostic tool, not a complete diagnosis. It supports thoughtful interpretation rather than substituting clinical judgment.
When You Should Seek Urgent Medical Evaluation
Some anion gap values should warrant immediate evaluation, especially when combined with symptoms or concerning context. Critical lab values on the blood chemistry panel, rapidly worsening severe acidosis, or an abnormally high gap in a patient who appears severely ill may point to a life-threatening underlying cause.
Immediate evaluation is particularly important if there is changed mental awareness, notable weakness, fainting, or shortness of breath. These signs can indicate that the body is not anymore responding adequately. Severe metabolic disturbances can advance fast, so holding off for symptoms to improve on their own can be risky.
If a calculation indicates a major abnormality, and the patient also has symptoms of dehydration, infection, toxin exposure, diabetic crisis, or kidney dysfunction, prompt medical review is appropriate. An abnormal gap alone does not tell the whole story, but in the wrong setting it can be a warning sign of a quickly progressing illness.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used to speed up lab interpretation by computing the gap from sodium, chloride, and bicarbonate values. It aids in evaluating acid-base disorders, especially unexplained acidosis, and can guide further testing. It is a useful medical evaluation aid, but it does not replace clinician assessment.
What does a high anion gap mean in unexplained acidosis?
A high result usually indicates metabolic acidosis from unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, and renal failure. The finding suggests acid accumulation rather than simple bicarbonate loss.
Can a normal anion gap still occur with acidosis?
Yes. A normal anion gap can still occur with acidosis, especially in hyperchloremic acidosis. Common causes include diarrhea, renal tubular acidosis, and other forms of bicarbonate loss. The patient can still be acidotic even if the gap remains within the reference range.
Why do albumin levels affect anion gap results?
Albumin contributes significantly to the pool of unmeasured anions in blood. When albumin is low, the raw gap may be falsely low or normal, which can hide an important problem. That is why the corrected anion gap is often more informative in patients with hypoalbuminemia.
When should an abnormal anion gap prompt urgent medical evaluation?
Urgent medical evaluation is warranted when an abnormal gap is accompanied by critical lab values, severe acidosis, altered mental status, or respiratory distress. Concerning symptoms, rapid worsening, or evidence of a serious underlying illness should not be ignored.